
Finding Your Ideal Training Volume: How Body Scans and Workout Data Changes the Way You Program
Your scale weight doesn’t tell you enough about muscle growth. BIA with segmental lean mass analysis tells you much more about what’s happening, and whether your program is actually working.
Key Points
Whole-body metrics like scale weight and even total lean mass are often too blunt to guide hypertrophy programming. Segmental lean mass (arms, trunk, legs) measured via bioelectrical impedance analysis (BIA) provides region-specific feedback.
By bracketing training programs with InBody scans, we can directly correlate training volume per muscle region with lean mass changes in the corresponding body segment.
With the right strategy, this can create a personalized dose-response curve: how much volume does THIS client need for THIS body part to grow?
Population-level volume guidelines (MV/MEV/MAV/MRV) are useful starting points, but individual variation is important.
The combination of segmental BIA data with per-exercise e1RM tracking gives coaches two independent signals (structural adaptation and neural adaptation) for a more complete picture of training response.
The Problem With Scale Weight
A client steps on the scale. They are up 3 pounds from last month. Is that muscle? Fat? Water? A large lunch? The scale cannot tell you, and neither can the mirror in the short term. This uncertainty creates a programming blind spot.
Total lean body mass (LBM) gets closer, but it has the same problem at a smaller scale. If LBM increases by 2 pounds, did it go to the chest? The legs? Is it evenly distributed? If your program emphasizes upper body hypertrophy but all the lean mass gain went to the lower body, your program is not doing what you think it is doing.
This is where segmental body composition analysis becomes much more helpful.
What DSM-BIA Actually Measures
The InBody 970S uses direct segmental multi-frequency bioelectrical impedance analysis (DSM-BIA) with 8-point tactile electrodes at six frequencies (1, 5, 50, 250, 500, and 1000 kHz). Unlike single-frequency BIA devices that estimate whole-body composition from a single impedance measurement, the 970S measures each of five body segments independently: right arm, left arm, trunk, right leg, and left leg.
This is not a trivial distinction. The trunk has fundamentally different tissue composition than the limbs (lower water content, more visceral organs, different fat distribution). Measuring it separately rather than extrapolating from a whole-body impedance value produces significantly more accurate regional estimates (Anderson et al., 2012).
For each segment, the InBody reports:
Lean mass in pounds — the amount of non-fat tissue (muscle, bone, water, organs) in that segment
Percentage of ideal — how the segment compares to population norms adjusted for height and sex
Fat mass — segmental fat distribution (not just total body fat percentage)
The lean mass values are what matter most for hypertrophy tracking. When a client's right arm lean mass goes from 8.2 lbs to 8.7 lbs over two months, that is roughly half a pound of tissue gain in a specific segment. Combined with knowledge of what they trained during that period, this becomes actionable programming data.
Bracketing Programs With Scans
At Verro, we scan clients approximately every 6 weeks, ideally before and after each training program. This creates what we call program bracketing: a before-scan and an after-scan that bound a known period of training.
The before-scan establishes the segmental baseline. The after-scan reveals what changed. The training program in between (which we have complete records of, including every set, rep, weight, and RPE) provides the dose. Now we have a dose-response relationship: X hard sets per week of chest work produced Y pounds of trunk lean mass change.
I should note, this is not a controlled experiment. Many confounders exist (nutrition, sleep, stress, illness, hydration status at the time of scanning). But across multiple programs, these confounders average out. After 4-5 program cycles with bracketing scans, clear patterns emerge for each client.
From Segments to Training Regions
InBody measures five segments, but training programs are organized around muscle regions: chest, back, shoulders, arms, quads, hamstrings, glutes, core. The mapping between these is not one-to-one.
Arms are straightforward, the InBody arm segment maps directly to the "Arms" training region (biceps, triceps, forearms). If arm lean mass increases and you have been training arms, the signal is clear.
Legs are a little more complex. The InBody leg segment contains quad, hamstring, glute, and calf tissue. If leg lean mass increases by 2 pounds, was it quads or glutes? The answer depends on what you trained. If 60% of your lower body hard sets targeted quads (squats, leg press, lunges) and 25% targeted glutes (hip thrusts, glute bridges), it is reasonable to attribute the lean mass change proportionally: roughly 1.2 lbs to quads and 0.5 lbs to glutes, but that is not always the case.
The trunk is the most complex. Chest, back, shoulders, and core all live in the trunk segment. A 4-pound trunk lean mass increase during a program where 40% of trunk-region volume was back work, 30% was chest, 20% was shoulders, and 10% was core would be attributed as: 1.6 lbs back, 1.2 lbs chest, 0.8 lbs shoulders, 0.4 lbs core.
Is this perfect? No. But it is a principled estimate based on available data, and it improves with each additional program cycle. It’s worth noting that Schoenfeld et al. (2019) have argued that regional hypertrophy can vary even within a single muscle depending on exercise selection, but fortunately our system also takes exercise selection, rep range, and intensity into consideration. However, from a volume point of view, this is a clear limitation.
The Volume Dose-Response Curve
The concept of a dose-response relationship between training volume and hypertrophy is well-established in the literature. Schoenfeld and Krieger (2017) conducted a meta-analysis showing a graded dose-response relationship between weekly sets per muscle group and muscle growth, with higher volumes producing greater hypertrophy up to a point.
The critical question for any individual is: where is that point for me?
Renaissance Periodization (RP) popularized the concept of volume landmarks: MV (Maintenance Volume), MEV (Minimum Effective Volume), MAV (Maximum Adaptive Volume), and MRV (Maximum Recoverable Volume), as reference points for programming. These are useful heuristics derived from coaching experience and literature synthesis. But they are population averages.
Israetel, Hoffmann, and Smith (2021) themselves acknowledge that individual variation in volume tolerance is substantial. A competitive bodybuilder may need 20+ sets per week for chest hypertrophy while a newer lifter achieves the same growth with 8 sets. Genetics, nutrition, sleep, stress, age, training history, and hormonal status all influence where someone falls on the dose-response curve.
This is where real data beats textbook numbers. When we have 5+ programs of volume-per-region data paired with segmental lean mass changes, we can plot each client's actual dose-response curve. The programs where they did high chest volume and gained trunk lean mass tell us where their MAV lives. The programs where they cut volume and maintained or lost lean mass tell us where their MV sits.
Two Signals Are Better Than One
Segmental lean mass is a structural adaptation signal: it tells you whether tissue was actually built. But it is not the only signal that matters.
Estimated one-rep max (e1RM) tracking provides a neural adaptation signal. When a client's bench press e1RM increases from 275 to 295 over a program, that reflects improvements in motor unit recruitment, rate coding, and intermuscular coordination, not necessarily chest hypertrophy. A stronger bench could result from better technique, better neural drive, or actual muscle growth.
Neither signal alone tells the full story. But together, they paint a complete picture:
e1RM up + lean mass up: The program worked. Both neural and structural adaptations occurred. This is the ideal outcome for a hypertrophy block.
e1RM up + lean mass flat: Neural adaptations driving strength gains without measurable tissue growth. This can happen during strength-focused blocks with lower volume, or when nutrition does not support growth.
e1RM flat + lean mass up: Structural growth without proportional strength gains. This can occur with high-volume, moderate-intensity hypertrophy work where the stimulus is metabolic rather than mechanical. The client is getting bigger but not yet expressing that size as strength.
e1RM down + lean mass down: Program was not effective. Volume may have been too low (below MEV), recovery insufficient, or external stressors (sleep, nutrition, life stress) undermined adaptation.
By tracking both signals across multiple programs, we build a nuanced understanding of how each client responds to different training stimuli. This is fundamentally different from programming by feel or by population averages.
Phase Angles: The Overlooked Metric
Beyond segmental lean mass, the InBody 970S reports phase angles at multiple frequencies (5, 50, and 250 kHz) for each body segment. Phase angle reflects the ratio of resistance to reactance in biological tissue and is considered a marker of cellular health and integrity.
Higher phase angles are associated with greater cell membrane integrity and more intracellular water, both indicators of well-nourished, metabolically active muscle tissue (Barbosa-Silva et al., 2005). In the context of hypertrophy tracking, segmental phase angles provide a qualitative complement to the quantitative lean mass data.
A client whose arm lean mass is increasing AND whose arm phase angle is improving is building high-quality muscle tissue. A client whose lean mass is increasing but phase angle is declining may be retaining water or experiencing edema rather than genuine hypertrophy. This distinction matters for programming decisions and nutritional guidance.
Norman et al. (2012) demonstrated that phase angle is an independent predictor of muscle function in clinical populations. While the research in healthy trained individuals is still developing, the theoretical basis for using phase angles as a tissue quality indicator is sound.
Practical Application: A Client Case
Consider a client who has completed five consecutive training programs over 10 months, with InBody scans before and after each program. Their data might look like this:
| Program | Training Focus | Chest Sets / Week | Trunk Lean Change | Bench e1RM Change |
|---|---|---|---|---|
| Program 1 | Hypertrophy | 10 | +1.8 lbs | +4.2% |
| Program 2 | Strength | 6 | +0.3 lbs | +5.1% |
| Program 3 | Hypertrophy | 14 | +2.4 lbs | +2.8% |
| Program 4 | Hypertrophy | 18 | +1.1 lbs | +0.5% |
| Program 5 | Deload / Pivot | 4 | -0.2 lbs | -1.0% |
From this data, several insights emerge:
MEV appears to be around 6-8 sets/week (Program 2 at 6 sets produced minimal trunk lean mass change, while Programs 1 and 3 at 10-14 sets produced clear gains).
MAV appears to be around 12-14 sets/week (Program 3 at 14 sets produced the best lean mass response).
MRV was likely exceeded in Program 4 at 18 sets/week — lean mass still increased but at a diminished rate despite higher volume, and strength gains nearly stalled. This suggests accumulated fatigue was outpacing recovery.
MV is below 4 sets/week (Program 5 showed a slight decline).
None of these insights are available from scale weight. None are available from total LBM. And none match the generic population-level recommendations exactly — this client's personal MAV of ~14 sets/week for chest is right in the middle of RP's hypertrophy range (8-20), but knowing the precise number allows for much more confident programming.
Limitations and Honest Caveats
This approach is not without limitations, and intellectual honesty requires stating them clearly.
First, BIA is not DEXA. Bioelectrical impedance is sensitive to hydration status, recent exercise, meal timing, and menstrual cycle phase. Standardizing scan conditions (same time of day, fasted, rested, after voiding) reduces but does not eliminate this noise. A single scan-to-scan comparison can be misleading; patterns across 4-5 scans are much more reliable.
Second, trunk segmentation is coarse. The trunk contains chest, back, shoulder, and core musculature, and BIA cannot distinguish between them. Our volume-proportional attribution model is a reasonable heuristic but not a precision instrument. MRI-based regional muscle volume measurement remains the gold standard for research purposes (Ogasawara et al., 2013).
Third, nutrition is a massive confounder. A client in a caloric deficit will not build much muscle regardless of their training volume. A client in a surplus may show lean mass gains that are partly water retention rather than contractile tissue. We do not currently track nutrition data, which limits the precision of the hypertrophy signal. This is an area we plan to address.
Fourth, the model improves with data. Two programs give you a trend. Five programs give you a curve. Ten programs give you genuine confidence. New clients start with population-based estimates; personalization emerges over months of training and scanning.
Where This Is Going
We are building toward a system where every client's volume landmarks are personalized, not based on what the average intermediate lifter needs, but based on what this specific individual has demonstrated through their own training history and body composition changes.
The research community is moving in this direction too. Damas et al. (2015) have called for more individualized approaches to resistance training prescription, noting that "inter-individual variability in muscle hypertrophy is substantial and should be accounted for in training program design." Dankel and Loenneke (2020) have argued that training studies should report individual responses, not just group means, because the range of responses to identical training protocols is enormous.
We agree. The future of evidence-based coaching is not better population averages: it is better individual data. And tools like segmental body composition analysis, combined with meticulous training tracking, bring that future within reach today.
Understanding Volume Thresholds
We talked a bit about it previously, but let’s dive in a little deeper to what volume thresholds are. The volume landmarks we reference throughout this article can be visualized through the lens of the Stimulus-Recovery-Adaptation (SRA) model. Each wave represents a training session: the dip is fatigue, the rebound is recovery, and where the wave settles relative to baseline tells you whether you adapted.
At different volume levels, these waves behave very differently:
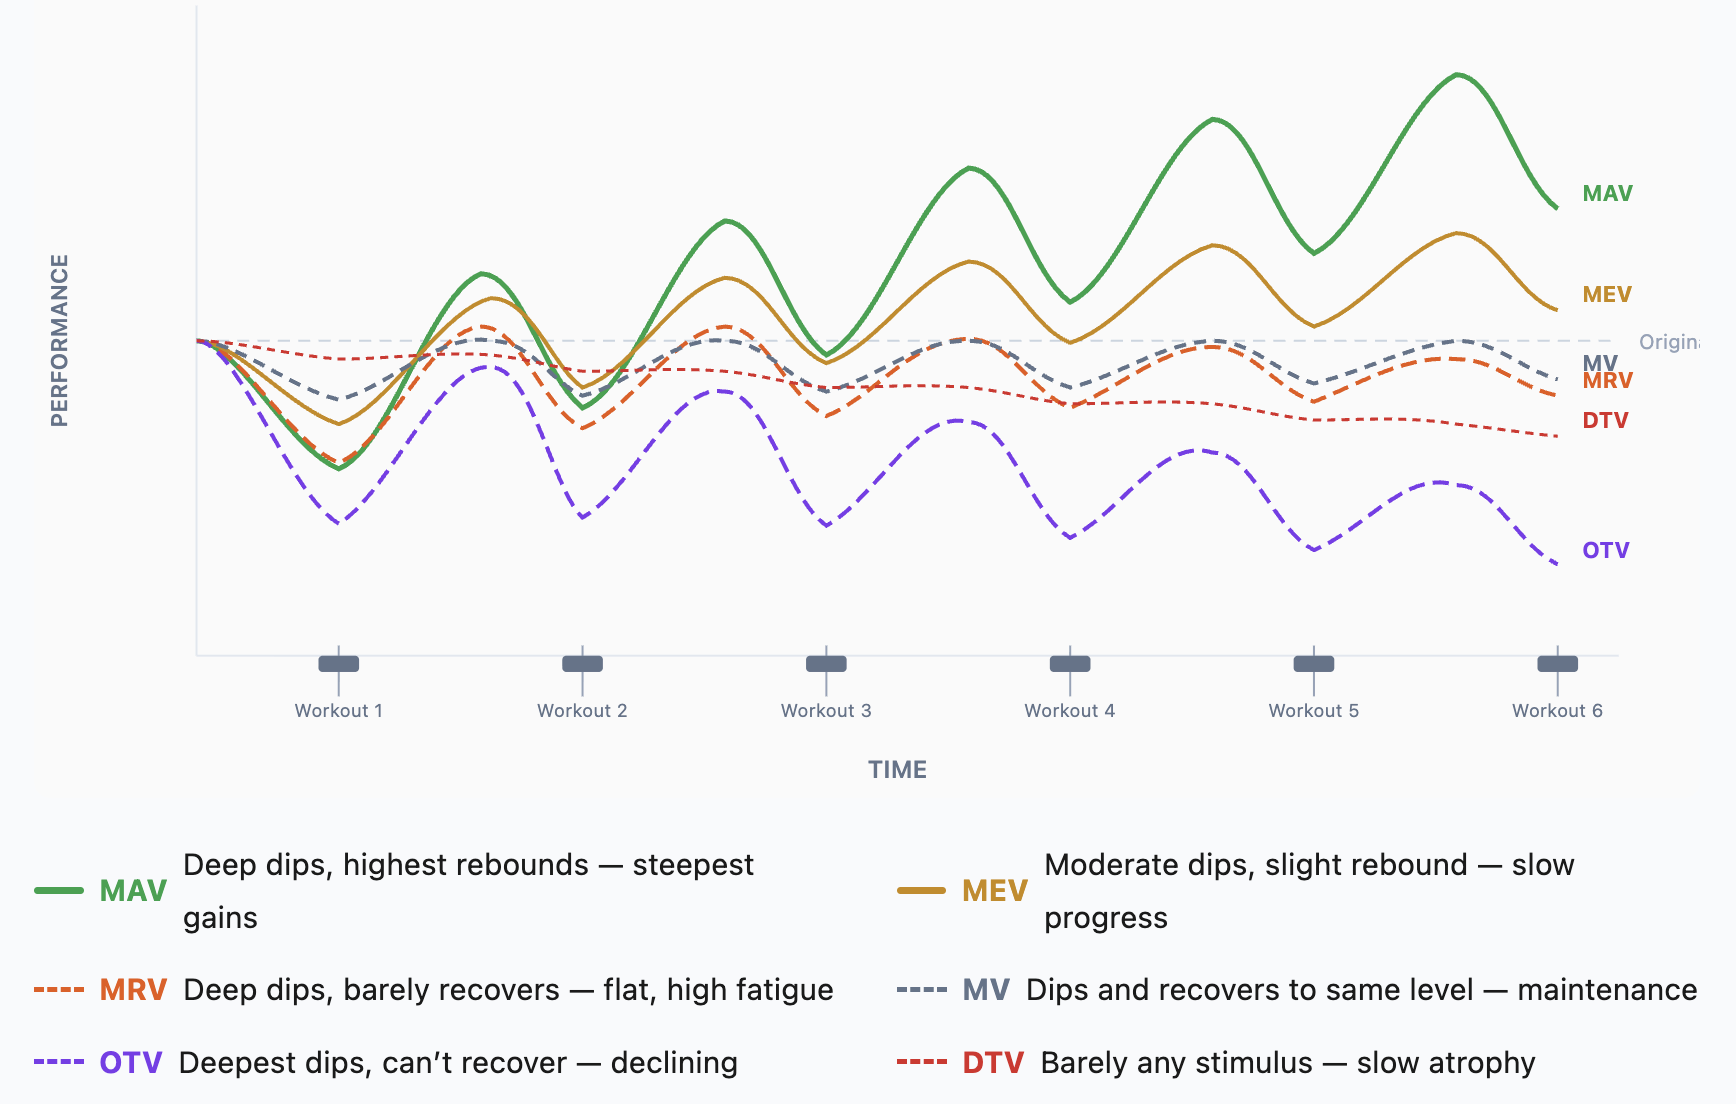
| DTV (Detraining) | Volume so low that adaptations are lost. The body regresses toward its untrained baseline. |
| MV (Maintenance) | Minimum volume to maintain current fitness. No growth, but no loss either. |
| MEV (Min Effective) | The threshold where adaptation begins. Below this, stimulus is insufficient to drive measurable change. |
| MAV (Max Adaptive) | The sweet spot. Best ratio of stimulus to recovery. This is the target zone for most training blocks. |
| MRV (Max Recoverable) | Upper limit before fatigue outpaces recovery. Usable in short overreaching phases, not sustainable. |
| OTV (Overtraining) | Volume exceeds recovery capacity. Performance declines, injury risk increases, health is compromised. |
Practical Takeaways
Get scanned regularly. Every 4-8 weeks, ideally before and after each training program. Consistency of conditions matters more than frequency.
Look at segmental data, not just totals. Total lean body mass hides where growth is (and is not) happening. Arm, trunk, and leg lean mass tell you what your program is actually doing.
Track training volume per muscle region. You cannot evaluate a dose-response relationship without knowing the dose. Sets per week per muscle group is the minimum tracking requirement.
Build your personal landmarks over time. After 3-5 programs with bracketing scans, patterns emerge that are more useful than any generic recommendation.
Use both strength and lean mass signals. e1RM tells you about neural adaptation. Lean mass tells you about structural adaptation. Together, they tell the complete story.
Be honest about confounders. One scan is a data point. Five scans are a trend. Do not overreact to single measurements, and always consider nutrition, sleep, and stress as variables.
References
| Citation (APA) | Study Type | Why It Matters | Supports This Claim |
|---|---|---|---|
| Anderson, L.J., et al. (2012). Validation of bioelectrical impedance analysis. British Journal of Nutrition, 107(S2), S1-S4. | Validation study | Validates segmental BIA against reference methods | Segmental measurement more accurate than whole-body extrapolation |
| Barbosa-Silva, M.C., et al. (2005). Population reference values for phase angle. American Journal of Clinical Nutrition, 82(1), 49-52. | Population reference | Establishes phase angle normative ranges by age and sex | Phase angle as a tissue quality marker |
| Damas, F., et al. (2015). Resistance training-induced changes in skeletal muscle protein synthesis. Sports Medicine, 45(6), 801-807. | Review | Calls for individualized training prescription | Inter-individual variability in hypertrophy is substantial |
| Dankel, S.J. & Loenneke, J.P. (2020). Analyzing differential responders to exercise. Sports Medicine, 50(2), 231-238. | Methodological | Argues for reporting individual responses, not just group means | Population averages hide enormous individual variation |
| Israetel, M., Hoffmann, J., & Smith, C.W. (2021). Scientific Principles of Hypertrophy Training. Renaissance Periodization. | Applied text | Defines MV/MEV/MAV/MRV framework | Volume landmarks as programming reference points |
| Norman, K., et al. (2012). Phase angle and impedance vector analysis. Clinical Nutrition, 31(6), 854-861. | Systematic review | Links phase angle with functional outcomes | Phase angle as independent predictor of muscle function |
| Ogasawara, R., et al. (2013). Continuous and periodic strength training. European Journal of Applied Physiology, 113(4), 975-985. | Experimental | MRI-based regional muscle measurement | Gold standard comparison for BIA estimates |
| Schoenfeld, B.J. & Krieger, J.W. (2017). Volume-muscle mass dose-response. Journal of Sports Sciences, 35(11), 1073-1082. | Meta-analysis | Quantifies the volume-hypertrophy dose-response curve | Higher volume = more growth, up to a point |
| Schoenfeld, B.J., et al. (2019). Regional muscle activation differences. JSCR, 33(11), 2995-3001. | Experimental | Shows hypertrophy varies within a single muscle | Exercise selection affects where growth occurs |
DISCLAIMER
This article is for educational purposes only and is not intended to diagnose, treat, or serve as medical advice regarding peptide use, hormone optimization, or any related therapeutic intervention. The compounds discussed in this article include both FDA-approved medications and unapproved research chemicals — their inclusion here does not constitute an endorsement or recommendation for use.
Peptide therapies carry real risks, including unknown long-term safety profiles, contamination from unregulated sources, and potential interactions with existing medications or medical conditions. The regulatory landscape around compounding pharmacies and peptide access is actively evolving, and legal availability may change.
Always consult with a qualified physician or endocrinologist before considering any peptide, growth hormone secretagogue, or related compound. Self-administration of injectable or oral peptides without medical supervision is strongly discouraged.
At Verro, we believe in evidence-based decision-making — which means being transparent about what the research actually supports and where the gaps are. We present this information so you can have informed conversations with your healthcare provider, not as a substitute for their guidance.





